An 8 months old domestic shorthair female cat was presented to the clinic with a history of listlessness, persisted vomiting, anorexia and dyschezia. On presentation, the cat was afebrile (38.8°C) and physical examination revealed depression, dehydration, pale mucous membranes. On abdominal palpation revealed severe abdominal pain and tensed abdomen.
A complete blood count (CBC) and routine serum biochemical analysis was done. The haematological parameters were well within the reference range with Haemoglobin-13.6 gm/dl; Total leucocyte count-8600/µl; Platelets- 3.80 x 10⁵/ µl; a normal differential leucocytes profile (Neutrophils- 36%, Lymphocytes-59 %, Eosinophils- 4% and Monocytes-1%). The serum biochemical analysis showed normal creatinine (1.3 mg/dl) and AST (42 U/l) values. The cat was administered with Ranitidine (@ 1 mg/kg b.wt. s/c) and Metoclopramide (0.2 mg/kg b.wt. i/m) to counteract vomiting and, fluid therapy (lactated Ringer’s solution @ 200 mL ql2h i/v) was given for correcting dehydration and improving tissue perfusion. Survey radiography did not show any abnormality. Barium sulphate contrast radiography was done at post 12 hours (Figure 1) and 24 hours (Figure 2) and 33 hours (Figure 3), linear streak barium stasis was noticed in intestinal loops. Then, it was decided for exploratory laparoenterotomy.
Preoperative stabilization was initiated with antibiotic injection. Cefazolin at 20 mg/kg i/m and Inf. Metronidazole at 10mg/kg i/v and fluid therapy with lactated Ringer’s solution @ 200 mL i/v). The cat was prepared for aseptic surgery on the ventral midline after premedication with Diazepam @ 0.5 mg/kg i/m. Induction and maintenance of anaesthesia was done with Isoflurane and oxygen mixture. A mid line Laparotomy is done to expose the abdomen, the intestinal loop is palpated and exteriorised out. Upon identification of the intraluminal mass enterotomy was performed and on thorough examination it was a linear foreign body. It was difficult to remove the foreign body completely because of its continuing cranial heading towards stomach. The stomach was opened and complete linear foreign body was removed. The gastrotomy and enterotomy wound were closed with inverted double layer pattern and simple interrupted knots inside the lumen respectively. The linear FB of around 105 cm made of string and thread was removed (Figure 4). Entire gastrointestinal tract was evaluated before closing. No areas of perforation or compromised vascular supply were observed and, therefore, intestinal resection was not necessary. Abdominal lavage was performed with warmed Normal saline solution and abdomen was closed routinely. The cat recovered from anesthesia without complications. Postoperatively food and water were withheld for 3 days and cat was maintained with parenteral nutrition which included crystalloids and colloids twice daily and antibiotic was continued for seven days post-surgery, later on advised to give liquid and semisolid food. Sutures were removed on 10th day of surgery. Animal recovered uneventfully.
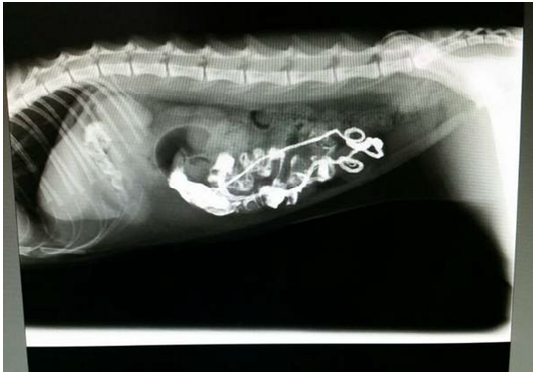
Figure 1: Lateral Radiograph after 12 hours of barium sulphate meal revealing pleated or plicated appearance of the intestinal loop suggestive of linear foreign body
Linear FBs produce a unique type of intestinal obstruction in small animals because they may cause serious and extensive damage to the intestinal tract contrary to the present case. Linear FBs are more commonly reported in cats than in dogs and in 90.6% cases of FBs are thread (Felts et al., 1984). In the present case, gastrointestinal obstruction due to linear foreign body was noticed in a cat which showed an uneventful recovery after prompt diagnosis and surgical intervention.
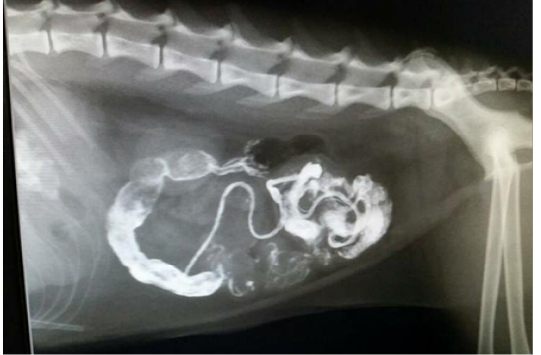
Figure 2: Lateral Radiograph after 20 hours of barium sulphate meal shows streaking of intestinal loop with barium
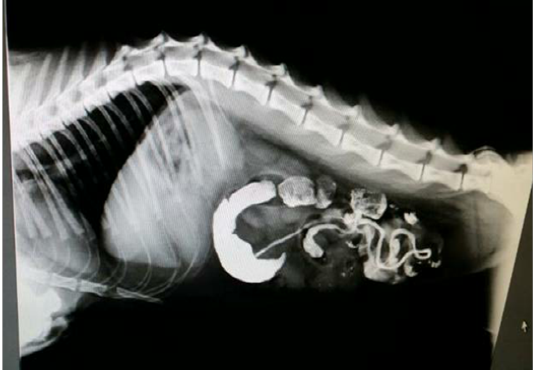
Figure 3:Lateral Radiograph after 33 hours of barium sulphate meal revealing accumulation of Barium in the intestinal loop and Barium has not passed into the rectum confirms intestinal obstruction
:
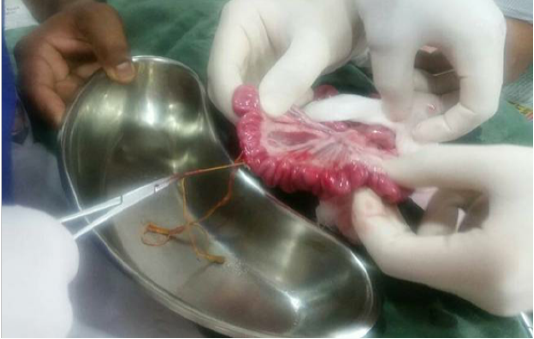
Figure 4: Surgical removal of linear foreign body

